Melatonin, Palbociclib, and Cyclin D1
Preclinical ER-positive breast-cancer study suggesting melatonin may blunt palbociclib-related cyclin D1 up-regulation and deepen G1 arrest
This page sits at the intersection of the melatonin hub and ER-positive CDK4/6 questions.
It covers the Zhuang et al. preclinical study of melatonin with Palbociclib in ER‑positive breast cancer.
The key finding is encouraging and specific.
In this model, Palbociclib reduced RB phosphorylation but paradoxically increased cyclin D1.
Melatonin pushed that signal in the opposite direction.
This is mechanistic and preclinical.
The findings come from cell lines and mouse models.
What the study found
Palbociclib reduced RB phosphorylation.
That is the expected on‑target effect.
At the same time, palbociclib alone paradoxically increased cyclin D1 expression in the model.
That is not good news.
It may reflect an early compensatory response.
When melatonin was added, it blunted the cyclin D1 up‑regulation seen with palbociclib monotherapy.
Melatonin also reduced cyclin D1, CDK4/6, and downstream RB/E2F1 signalling.
In cell culture, the combination produced stronger G1 arrest and stronger anti‑proliferative effects than either agent alone.
In a mouse xenograft model, melatonin plus palbociclib reduced tumour volume and tumour weight more than palbociclib or melatonin alone, which the authors described as a synergistic antitumour effect in that experimental setting.
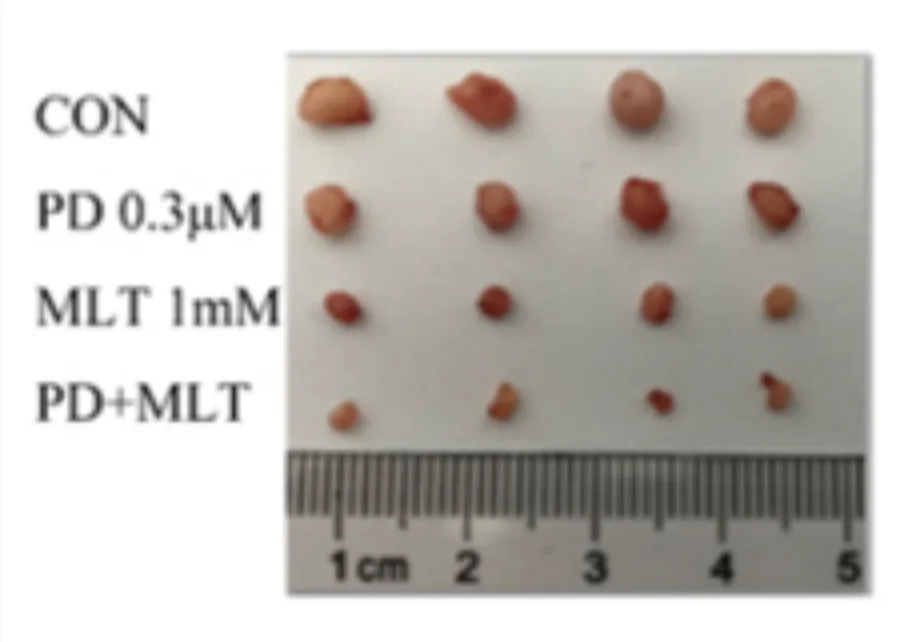
Zhuang, Z., Tang, Q., Gong, M., Pan, J., Yuan, X., & Yuan, Y. (2024). Melatonin enhances the efficacy of CDK4/6 inhibitor in breast cancer cells via down‑regulating the expression of cyclin D1. Biomedical Journal of Scientific & Technical Research, 59(3), 9367–9378. https://doi.org/10.26717/BJSTR.2024.59.009367
Why this matters in ER+ disease
Cyclin D1 sits upstream of the same CDK4/6–RB axis that many ER‑positive tumours rely on.
If a treatment lowers RB phosphorylation but tumour cells respond by raising cyclin D1, that can look like an early adaptive survival move.
It suggests melatonin may not just add general anti‑proliferative pressure.
It may also counter one specific compensation route.
Bottom line
Palbociclib alone may increase cyclin D1 in some models.
Melatonin may push that signal back down while deepening G1 arrest, CDK4/6, inhibition and downstream RB/E2F1 signalling.
In mice, the combination also shrank tumours more than either agent alone in this particular model.
That makes the combination biologically interesting and potentially powerful.
It remains a preclinical finding until stronger human data appears.
Study source
Melatonin Enhances the Efficacy of Cdk4/6 Inhibitor in Breast Cancer Cells Via Down-Regulating the Expression of Cyclind1
https://biomedres.us/fulltexts/BJSTR.MS.ID.009367.php
Q. What dose did the mice receive?
Palbociclib (PD‑0332991):
125 mg/kg
Given orally (by gavage)
Once daily
Melatonin (MLT):
40 mg/kg
Given intraperitoneally (i.p.)
5 days per week
Combination group:
Palbociclib 125 mg/kg orally, daily
Plus melatonin 40 mg/kg i.p., 5 days per week
How long were the mice treated?
The paper describes that once tumours reached a certain size, mice were randomised into four groups (control, palbociclib, melatonin, combination).
Treatment with PD, MLT, or PD + MLT was given for 2 weeks (14 days) before the mice were sacrificed and tumour weight/volume were measured.
So, in simple terms:
Duration: about 2 weeks of treatment after randomisation
Outcome: after those ~2 weeks, the combination group had significantly smaller tumour volumes and weights than either palbociclib alone or melatonin alone, which the authors described as a synergistic anti-tumour effect in that model.
This information is for education only. It is not medical advice, diagnosis, or treatment. Please speak with a qualified clinician before making changes to care, medication, or supplement use.
© 2026 Abbey Mitchell. All rights reserved. Please share by URL rather than copying page text.
Related pages
Melatonin hub pages
Melatonin in Oncology - Study Notes — the hub page that ties together the mitochondria, dosing, immune, phase-separation, and fibrosis sections
Dosing, Bioavailability, and Human Scaling — how mouse and cell data translate into estimated human exposure, route limits, and bioavailability caveats
High-Dose Mitochondria, RET, and ROS — the mechanistic RET, ROS, uncoupling, and apoptosis sequence behind the high-dose claim
Moderate-Dose Immune Effects and Timing — the human oral adjunct literature, Th1 logic, and timing framework
Disease-specific context
ER-Positive / HER2-Negative — broader ER-positive disease context for where this preclinical combination question may matter
CDK4/6 Options and Supplement Considerations — practical context on CDK4/6 therapy and supplement-related considerations
SONIA Trial and CDK4/6 Timing — timing and sequencing context for CDK4/6 use in ER-positive disease
Galectin‑3, Cyclin D1, Modified Citrus Pectin(MCP) and CDK4/6: A Patient Guide — related cyclin D1 context for readers comparing different ways to pressure the CDK4/6 axis
Return to the A–Z directory of
evidence-based research summaries and
practical support resources